The New York City Department of Health and Mental Hygiene (NYC DOHMH) will provide almost $9 million to nonprofits in the city that provide gender-affirming care for minors to fill the gap left by major hospitals that have capitulated to the Trump administration and stopped providing these essential services.
City records explaining the funding emphasize the “compelling need for gender-affirming care services” that necessitates the expedited process NYC DOHMH plans to use – called a negotiated acquisition.
“NYC Health will contract with organizations providing or facilitating the provision of gender-affirming care to patients under age 18,” the department states. “This includes the prescription and administration of puberty-blockers and hormone replacement therapy to all minor patients for whom such services are medically necessary based on the prevailing standards of care. Services will be performed by qualified medical providers with current New York State licensure, and will be provided consistent with state laws governing parental consent.”
The department has identified two potential groups, Callen-Lorde Community Health Center and Nonprofit Organization for Philanthropic Initiatives (NOPI), to enter into a three-year contract to help direct funds to vendors that offer the proper services. The contract would begin on February 1, 2027. The department also invited others who believe they can provide these services to email Tamala Watson at twatson2@health.nyc.gov by October 16 at 2:00 pm.
According to Gothamist, the money is part of Mayor Zohran Mamdani’s (D) $15 million plan to expand access to gender-affirming care for trans youth. Announced in June, the plan includes three initiatives: establishing a direct access care fund; creating a call and text line to connect people with resources; and research to identify health care access gaps.
Trans journalist and activist Erin Reed celebrated the $9 million investment on Bluesky. “I do believe the city can be doing much more, but this is a wonderful start from Mayor Mamdani,” she said.
News of the funding dropped only two weeks after dozens of protesters – including trans actor Elliot Page – gathered outside NYU Langone Health, one of three New York City hospitals that recently caved to the Trump administration by ending gender-affirming care for trans youth. Two weeks before that, hundreds gathered outside New York City’s Mount Sinai Hospital to express their anger at its decision to permanently stop gender-affirming care for youth in a move many said was “bending the knee” to the Trump administration.
The DOJ began issuing civil subpoenas to hospitals around the country in 2025, attempting to obtain personal medical records for trans youth and threatening federal funding for hospitals that continued to provide the care.
According to the DOJ, its “nationwide investigation into the child gender-transition industry” has examined “potential violations of the Food, Drug, and Cosmetic Act, the False Claims Act, and other federal health care laws, including fraudulent billing practices such as the use of false diagnosis codes to obtain payment from federal health care programs and private insurers.”
But critics say these investigations amount to “fishing expeditions” aimed at finding reasons to prosecute health care providers in states where pediatric gender-affirming care remains legal, and to intimidate providers into ending pediatric gender-affirming care programs.
This November, voters in six states will decide on eight LGBTQ+-related ballot measures, including four anti-trans sports bans in Colorado, Arizona, Nebraska, and Washington; two measures restricting gender-affirming care for transgender youth in Colorado and Missouri; a measure that could out LGBTQ+ kids to their potentially unsupportive parents in Washington; and one pro-LGBTQ+ measure to remove a state same-sex marriage ban in Virginia.
“This isn’t actually about giving voters a say in democracy. It’s a political tactic by a small but vocal minority of extremists who want to turn out their base, driven by the fear and misunderstandings about people who are transgender,” said Adam Snipes, the director of strategic partnerships at the Ballot Initiative Strategy Center, during a September 30 GLAAD media briefing attended by LGBTQ Nation.
Snipes is correct: anti-trans measures are being used as “ballot candy” to increase Republican turnout at the polls.
But statewide anti-trans proposals have dramatically increased since 2015, the year that the US Supreme Court legalized marriage equality. In 2016, North Carolina passed an anti-trans bathroom bill. Since then, similar anti-trans measures have expanded to sports, educational policies, healthcare, and other areas.
Approximately 91% of anti-trans bills fail in state legislatures, GLAAD’s senior director of news and campaigns Barbara Simon said. But such legislation and ballot measures give anti-LGBTQ+ politicians and activists “a permission slip” that emboldens them to use marginalizing and dehumanizing rhetoric that harms vulnerable youth, Simon said.
“This is really part of a national MAGA playbook, which is about distracting voters from real issues facing families — like high healthcare costs, gas costs, housing costs — and instead just flaming fears about a small, really already vulnerable group of people… in this case, LGBTQ+ kids,” Washington’s first out lesbian state House Speaker, Rep. Laurie Jinkins (D), told the press briefing.
Anti-trans sports bans in Colorado, Arizona, Nebraska, & Washington
Colorado, Arizona, Nebraska, and Washington are all considering ballot measures with nearly identical language that would ban students who are transgender from playing school sports on sex-segregated teams that differ from the sex they were assigned at birth. None of these measures take intersexuality into account, leaving intersex students unsure about their place on the sports field.
Generally speaking, these measures fall largely on young girls and women to “prove” their sex, often with invasive medical exams that aren’t usually part of standard athletic exams. (Athletic medical exams usually focus on athletes’ eyesight, bone health, as well as respiratory, cardiovascular, or other issues that could affect overexerted athletes.)
Medical examinations to verify athletes’ sex can violate the privacy of all young girls and women — causing a decrease in their sports participation overall. Furthermore, such exams may not be covered by patients’ health insurance plans, adding an extra financial burden for low-income families.
These measures undermine local control by overriding policies and recommendations already put in place by local school boards and associations that have articulated what’s best for their students’ needs. These ballot measures also do nothing to address the sexism, abuse, and poor funding that harm girls and women and discourage them from participating in sports to begin with.
Arizona’s Proposition 318
Based on a 2022 Arizona law that federal courts had blocked from enforcement (before the US Supreme Court ruled such bans as constitutional last June), the so-called “Protect Girls’ Sports in Arizona Act” would require K-12 schools and private sports leagues to designate which sports are sex-segregated and then decide participation based on the sex listed upon each player’s birth certificate.
Additionally, schools and private leagues would have to ban trans athletes from restrooms, showers, and locker rooms that don’t match the sex they were assigned at birth. The measure would allow athletes to sue schools or leagues that violate its provisions.
Darrell Hill, the policy director for ACLU of Arizona, told KTAR that facilities and cities could interpret the law too broadly and restrict restroom and locker room access to trans kids and adults in various situations that have nothing to do with sports participation. “It can really act as a big barrier for trans people to participate in public life,” he said.
While the measure seems to “verify” athletes’ sex via birth certificates, state Sen. Mitzi Epstein (D) said it would “subject girls to invasive inspections and questions about their gender,” effectively harming all girls and women (and communicating that they are less valued than boys and men), “in an effort to score political points by discriminating against trans girls.”
The Arizona Interscholastic Association says no trans student-athletes have tried to compete in the state since the 2022 law was signed. It’s unclear whether any tried to compete before the 2022 law was signed.
Colorado’s Proposition 134
Proposition 134 would then require K-12 schools, colleges, and athletic associations to designate sex-segregated and co-ed sports and then forbid boys from participating on girls’ teams and vice versa.
The measure would define girls as people with female reproductive organs and boys as those with male reproductive organs, but it’s unclear how sex would be determined. While some supporters say a doctor-signed form or a DNA cheek swab could suffice, opponents warn that it could subject girls to invasive genital inspections.
Z Williams, a school parent and director of Bread and Roses Legal Center, told The Colorado Sun, “Kids have been playing sports with trans kids for decades…. Playing sports is an important and healthy part of growing up: People building a sense of who they are, learning how to work with a team, learning to lose. To take that away from kids simply for who they are is absurd. It is socially and politically cruel.”
Chris Cook, the father of an 11-year-old transgender girl, told the aforementioned publication, “It would tell kids that simply participating in school sports could mean being questioned, scrutinized, or subject to invasive gender inspections to prove who they are. No child should have to live with that fear, and this doesn’t affect (just) transgender kids. When schools are asked to police students’ gender, any child who looks too tall, too strong, or doesn’t fit someone’s idea of what a girl should look like could be singled out.”
Nebraska’s Measure 442
Measure 442 would write into the state constitution a 2025 law, sponsored by state Sen. Kathleen Kauth (R), that already requires public K-12 and college athletes to play on teams matching their sex at birth. The measure defines one’s sex at birth as having a reproductive system that “does or at some point will produce, transport, and utilize” either eggs ( for a woman or girl) or sperm (for a man or boy).
The measure would apply to all athletic teams or sports sponsored by public schools, postsecondary educational institutions, private schools, or educational institutions that compete against public schools.
Interestingly, the state Supreme Court recently heard arguments challenging the measure’s legality. Opponents say that the ballot measure’s sponsors failed to “adequately inform the public of what they are trying to accomplish” when collecting signatures for the effort. The measure will appear on ballots regardless of the court’s decision; if the court rules against it, all votes upon it will simply be invalidated.
Washington’s Initiative IL26-638
IL26-638 would bar students who are “biologically male” from competing in K-12 schools and nonprofit sports teams designated for girls and women. The initiative would require every student who wants to compete in girls’ sports to obtain a signed statement from a health care provider verifying their sex. Students wanting to play on boys’ teams wouldn’t have to obtain any such statement.
The initiative permits three verification methods: genetic testing, testosterone measurement, or a visual examination of reproductive anatomy. Seeing as the first two methods are expensive and not covered by insurance, most parents will likely go for the third option, requiring kids to expose their genitals to adult medical professionals.
Over 100 doctors and other medical professionals recently released a statement against the initiative, with some saying they would refuse to conduct invasive exams to verify the sex of young girls and women.
“IL26-638 would make every girl in Washington who wants to compete in a female-only interscholastic sport prove her sex to a doctor, regularly, in order to play,” the Washington State PTA noted, calling the initiative “discriminatory,” “harmful,” and “disproportionate.”
Trans journalist Erin Reed noted that even if the measure passes, it could still face constitutional challenges under the longstanding legal precedent of Washington laws protecting trans students.
“Washington adopted an Equal Rights Amendment in 1972 declaring that ‘equality of rights and responsibility under the law shall not be denied or abridged on account of sex,’” Reed wrote. “That provision triggers strict scrutiny for claims of sex discrimination, a standard that would likely render a categorical ban on transgender participation in sports unconstitutional — particularly given the state’s more liberal judiciary.”
Restricting gender-affirming healthcare in Colorado and Missouri
Two states, Colorado and Missouri, both have ballot measures to restrict gender-affirming healthcare for trans youth. However, they differ in significant ways.
Colorado’s Proposition 135
Colorado’s Proposition 135 is a vaguely written measure that would forbid doctors from performing surgeries on anyone under 18 “for the purpose of altering biological sex characteristics,” including changes to sexual organs, body shape, facial appearance, or voice (even though such surgeries on minors are rare to nonexistent).
The measure would also ban state or federal funds, Medicaid, and private insurance from paying for these surgeries. Though the measure’s language doesn’t specifically mention transgender youth, its restrictions would apply to any young person. However, the law wouldn’t place any restrictions on prescribing hormone therapy, puberty blockers, counseling, or support for social transition.
The measure includes exceptions for male circumcision, people born with a “medically verifiable disorder of sex development,” and “acquired physical or chemical abnormalities,” meaning that intersex individuals could still be eligible for augmenting surgeries.
Nevertheless, the Colorado Medical Society opposes the measure (along with dozens of other LGBTQ+ and allied organizations statewide), saying it would interfere with doctors’ medical judgment. The measure is backed by Protect Kids Colorado, an organization led by anti-LGBTQ+ activist Erin Lee.
Jax Gonzalez, political director at One Colorado, said the measure’s vague language around a minor’s “perception of sex or gender” leaves both patients and providers unclear about what procedures would be prohibited.
“All of us have gender and have lots of ideas about that, and so, does that mean that if a patient brings up a conversation about their own gender, regardless of their general identity, does that mean that that provider can’t treat them anymore?” Gonzalez, who is trans, told News From the States.
Missouri’s Amendment 3
Missouri’s Amendment 3 main purpose is to repeal the abortion-rights amendment that voters approved in 2024 and to make most abortions illegal in the state, except for ones that are conducted in cases of medical emergencies, fetal anomalies, and within the first 12 weeks of pregnancies caused by rape or incest.
The final clause in the measure would “prohibit gender transition procedures for minors,” which is curious, seeing as the state has banned gender-transition surgeries for minors since August 2023. The measure would also ban puberty blockers and hormone replacement therapy for minors.
Currently, state law forbids any new prescriptions of the aforementioned medications for trans youth until 2027; the measure would write this ban into the state constitution, meaning it would continue indefinitely.
Forcibly outing trans students to their parents in Washington
Washington voters will consider IL26-001, a measure that would repeal the state’s current parents’ rights laws and replace them with language taken verbatim from Louisiana. The measure would give parents unrestricted access to school, medical, and mental health counseling records without requiring student consent, including information on confidential conversations about a child’s sexual orientation or gender identity.
“When a student … is dealing with anxiety, they need trusted adults and mental health resources they can turn to that help them make sense of their world,” the American Civil Liberties Union (ACLU) of Washington wrote in opposition to the measure. “[Allowing parents to view sensitive counseling records is a] violation of privacy [that] can undermine the relationships that students may have with counselors and other trusted adults in schools.”
“The sad truth is not all students have a supportive adult they can turn to and talk about their sexuality, gender identity, or mental health without fear. Allowing schools to disclose private health information — as IL26-001 proposes — would severely impact a student’s stability at home, at a time when they need love and support, not punishment and rejection,” the ACLU of Washington added.
Indeed, statistics show that 40% of homeless queer youth say they were kicked out of their homes when their families learn of their identities, meaning that the measure could worsen at-home conflicts for LGBTQ+ students with unsupportive or abusive parents.
This initiative and the state’s ballot measure banning trans athletes are opposed by state Gov. Bob Ferguson (D), the state’s US Sen. Patty Murray (D), the Washington State Parent-Teachers Association (PTA), by the Washington State Nurses Association, the League of Women Voters, and domestic violence prevention groups, because they put kids at greater risk of violence and harm.
Defending marriage equality in Virginia
A bright spot on the somewhat gloomy horizon, Virginia’s Question 2 asks voters to remove the state’s 2006 constitutional ban on same-sex marriage and to add a right to marry regardless of a partner’s sex, gender, or race.
The state’s current ban, rendered inactive by the US Supreme Court’s 2015 Obergefell v. Hodges decision legalizing marriage equality, defines marriage as “only a union between one man and one woman” and bans any union, partnership, or legal status for unmarried couples that carries the rights and benefits of marriage. Question 2 would remove all of this language and acknowledge that “Marriage is one of the vital personal rights essential to the orderly pursuit of happiness.”
Virginians approved their state’s same-sex marriage ban in 2006, with 57% voting yes. A federal judge struck it down in 2014, but it stayed in the state constitution. State election officials say the ban would become enforceable again if the US Supreme Court ever overturned Obergefell v. Hodges, as some of the court’s conservative justices have threatened.
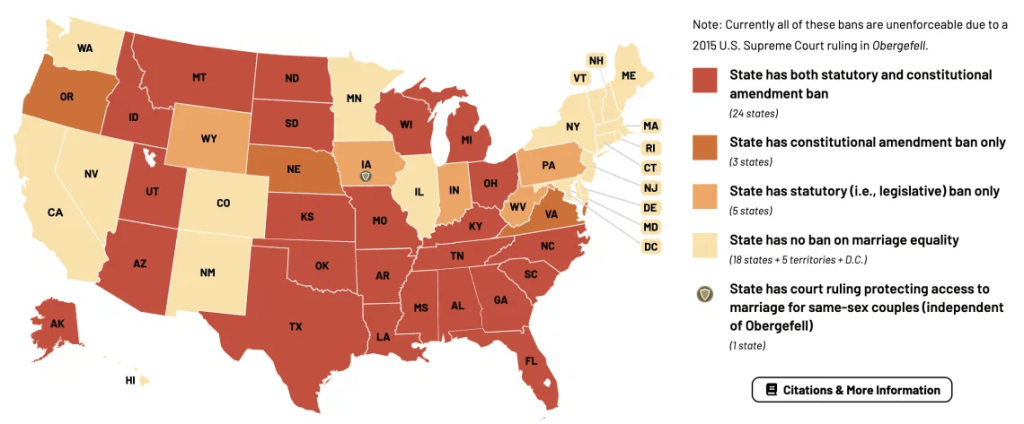
Currently, 24 states have dormant bans against same-sex marriage in both their state constitution and their statutes, five have such a ban in their statutes only, and three have such a ban in their constitution only, according to the Movement Advancement Project.
Since 2020, voters in four states have voted to repeal previously approved same-sex marriage bans. Nevada did in 2020, and California, Colorado, and Hawaii all did the same in 2024.
These ballot measures are about LGBTQ+ involvement in civic life
“As somebody who grew up trans, sports and other activities represented more than just competition,” Adrianna Suluai, the Policy & Advocacy Director at UTOPIA Washington, an organization dedicated to uplifting queer and transgender Pacific Islanders, told the press briefing.
“They were opportunities for me to participate, build confidence, and be around other young people and feel like I was a part of something. And when you’re a young person who may already feel different, sometimes simply having a place where you can show up and belong means everything,” Suluai added.
Suluai’s comment applies not only to the sports field but also to LGBTQ+ youth in classrooms, doctors’ and counselors’ offices, and the general public.
Because these ballot measures are often sold as ways to “protect children’ and strengthen “parental rights,” it’s all the more imperative that LGBTQ+ voters and allies understand them and share their potentially harmful consequences with other sympathetic voters.
A First Nation says it aims to defy Alberta Premier Danielle Smith’s government by establishing a safe haven for gender-affirming medical care.
Leaders of the Saddle Lake Cree Nation say access to health care is a treaty right and falls under its inherent jurisdiction.
Late last year, Smith’s United Conservative Party government used the Charter’s notwithstanding clause to shield its legislation from court challenges.
The law prohibits doctors from prescribing puberty blockers or hormone therapy to transgender and gender diverse children under 16.
The premier has said its aim is to protect children and their fertility. Doctors and national medical associations have pushed back, noting puberty blockers don’t render a person infertile.
This week, during a gathering to mark 150 years since the signing of Treaty 6, Saddle Lake Chief Dale Steinhauer said the law is one of many that are dehumanizing.
“No longer will our children and families have their rights taken away,” she announced at Fort Pitt Provincial Park, Sask., on Wednesday.
“When one group’s rights are removed, we are all affected.”
The nation, located 170 kilometres northeast of Edmonton, said it’s working to attract clinicians to provide care on its reserve land.
It has also started fundraising to develop its health law and defend it against potential legal challenges.
Steinhauer said clinicians who provide gender-affirming care on reserve land would be exempted from sanctioning by regulatory bodies.
“To the medical profession and regulatory bodies like the College of Physicians and Surgeons of Alberta: when will you stop this violence?” she said.
An email statement from the college said the organization respects Steinhauer and recognizes the treaty rights of all First Nations, as well as the rights and interests of transgender minors and their families.
“CPSA will continue to support regulated members in understanding their professional responsibilities while providing respectful, compassionate and evidence-informed care within the bounds of applicable legislation, including laws that apply to the treaty rights of First Nations.
When asked on Thursday, Smith said she doesn’t have any authority over the First Nation and respects its sovereignty.
“They are an independent nation, so I’ll be interested to see if they’re able to attract a doctor to do that,” Smith said while attending the Alberta Industrial Heartland Association annual conference in Edmonton.
‘I would have loved to have me as a doctor’
Dr. James Makokis, a two-spirit family physician from Saddle Lake Cree Nation, became emotional at the announcement while speaking about the impact of violence against two-spirit and transgender people, including self-harm.
“That is a public health emergency that has to stop,” said Makokis.
“When there’s a threat to the buffalo calves in the herd, all of the adult buffalo form a circle around those young ones, because they’re the next generation.”
Makokis said providing young two-spirit people with proper gender-affirming care is one way to combat high rates of suicide and other “horrible statistics” affecting the community.
“If I had someone that looked like me, that had braids like me, that spoke Cree like me, that understood our medicine and our ways of being, that would have been incredible,” said Makokis.
“I would have loved to have me as a doctor.”
For parents like Tyler Youngchief, councillor for Kehewin Cree Nation, Steinhauer’s announcement hits close to home. His seven-year-old son, Presley Miyoskwam Napew Youngchief, came out as transgender at the age of three.
“The moment he started vocalizing he was a boy and that’s who he is, there was no hesitation between my spouse or myself or his siblings,” Youngchief told CBC News. “It was just full-on acceptance right from our whole family.”
But both Youngchief and Makokis know the road to creating a gender-affirming care safe haven won’t be easy.
Youngchief said bullying in the form of homophobia and transphobia directed at Presley are his biggest concerns for the future.
Makokis added that fear is a familiar feeling for marginalized groups like trans and two-spirit people.
“It’s really important for us as individual clinicians, as individual physicians, as citizens of this democratic country known as Canada, for people to stand up,” said Makokis.
“Sometimes that means as individuals we have to risk losing some of our own individual freedoms, and in my case that could be my medical licence.”
Steinhauer cited the medicine chest clause unique to Treaty 6, which says the Crown will keep a medicine chest in the home of each federal government agent working on or near a reserve.
It’s widely understood by First Nations to be a commitment to provide comprehensive health care, and Indigenous leaders have criticized the Crown for failing to live up to the promise.
Steinhauer asked how the Alberta government could stop First Nations doctors from practising, or accessing the medicine chest.
“Have the colonial governments not learned enough from their own history?”
Alberta’s health-care law is one of three from the UCP government impacting transgender people across the province.
Another requires parental consent for students under 16 to change their names or pronouns at school. The third bans transgender athletes 12 and older from participating in amateur competitive female sports.
NDP MLA Brooks Arcand-Paul, who represents Edmonton-West Henday and is shadow minister for Indigenous relations, said the Alberta NDP support Saddle Lake Cree Nation’s exercise of sovereignty.
“As a two-spirit person, I wish I had this protection when I was younger. I wish I had this understanding that our two-spirit kin are scared,” Arcand-Paul told CBC News. “I wish I didn’t have to think I did not belong here.”
A coalition of blue states has come together to file a lawsuit against the Trump administration challenging its plan to strip federal funds from gender-affirming care for minors. The lawsuit alleges that the administration is overstepping its authority by trying to dictate what medical procedures can and can’t be covered by federal funding.
“[The Department of Health and Human Services (HHS)] has disregarded the law and its own policy precedent in another attempt to restrict transgender individuals’ access to crucial care,” California Attorney General Rob Bonta said in a statement. “We will not stand by as the Trump administration oversteps its authority and twists the facts to justify its bad-faith agenda against transgender Americans. We will continue to fight to secure access to medically necessary care and protect transgender individuals’ abilities to prosper as their authentic selves.”
The lawsuit targets Robert F. Kennedy Jr. as the head of HHS, as well as Dr. Mehmet Oz in his role as administrator of the Centers for Medicare & Medicaid Services (CMS). Last month, the departments finalized a plan to prevent federal Medicare and Medicaid plans from covering gender-affirming care for anyone under the age of 18, and to bar plans under the federal Children’s Health Insurance Program (CHIP) from covering the care for anyone under 19.
The plan spent months in a public comment period during which is received nearly 35,000 comments, over 90% of which opposed the plan. Despite this, the rule is set to go into effect on October 13 with little change to the text of the final document.
The lawsuit wastes no time highlighting to the US District Court for the District of Massachusetts that the administration’s new plan is not about healthcare, but an attack on trans people.
The introduction states, “The Administration seeks such broad and unprecedented powers in part to advance its social policy agenda, a key component of which involves relentless attacks on a small and vulnerable population—transgender individuals—whose very existence the President scapegoats to stoke national division.”
The lawsuit makes a case that the proposed rule oversteps states’ rights by regulating the practice of medicine, a responsibility that both Congress and existing legal precedent have made clear is reserved for the states themselves. The suing states also say that HHS has cherry-picked its evidence and failed to make a case for its ban on gender-affirming care funding, and that the plan change violates the Social Security Act and HHS precedent by excluding care that has been deemed medically necessary by the states.
The lawsuit also highlights that Congress left the decision for what should be covered by Medicare and CHIP to the states, and therefore the federal government cannot simply impose a rule to prevent the states from exercising their own will.
“The federal government does not have the authority to dictate what medically necessary care New York provides to its residents,” said New York Attorney General Letitia James in a statement. “This unlawful rule threatens access to health care for transgender young people and undermines states’ ability to administer our own Medicaid programs. New York will continue to stand up for patients and defend our authority to provide the care they need.”
The lawsuit additionally includes a nod towards a longstanding argument that banning gender-affirming care is discrimination based on sex, as under the proposed rule cis patients will still be able to receive coverage for the same treatment and care that is being denied to trans patients.
In his statement, Attorney General Bonta was keen to highlight that this proposed rule does not stop anyone from practicing gender-affirming care in any state where it is still legal (which includes California). The only restriction is on the use of federal funds, and the rule explicitly still allows for state funds to be used for the care.
An earlier HHS attempt saw the department pushing a rule that would have barred hospitals and clinics that provided gender-affirming care from receiving any form of federal funding at all. However, a judge struck that rule down in April and the Trump administration seemed to back off from trying to appeal that ruling in July.
Trans journalist Erin Reed called the states’ lawsuit “the next major step in the fight to protect transgender healthcare,” since the removal of federal funding would be ” a virtual death sentence for any hospital system.”
Reed noted that over “40 hospitals and health systems have stopped or paused their programs in capitulation” to the administration despite there being no federal law against the care. Some of these institutions have stopped providing the care in violation of state or local laws that explicitly protect transgender people from healthcare discrimination.
The federal agency that runs Medicaid and the Children’s Health Insurance Program will no longer pay for gender-affirming care for minors who don’t identify with the sex they were assigned at birth.
The Department of Health and Human Services announced Aug. 12 that it finalized a rule after more than a year of taking steps to use the federal government’s power to limit this type of medical care.
“We are not going to pay for our innocent children to undergo these barbaric surgeries and practices, which result in unthinkable and irreversible harm to their young bodies,” President Donald Trump wrote in a social media post.
The rule goes into effect Oct. 13 and includes a six-month grace period for children with government insurance who are currently using hormone therapy, according to HHS. It does not affect mental health coverage.
“Children deserve our protection, not experimental interventions that pose serious risks and convey no proven benefits,” Dr. Mehmet Oz, who runs the Centers for Medicare and Medicaid Services, said in a news release. He said the move is “protecting children from potentially irreversible harm.”
HHS did not say how much federal money it currently spends on surgeries, puberty blockers or hormone therapy, or how many children enrolled in government health insurance are receiving gender-affirming care.
Most gender-affirming care is sought by young adults, not children, but as many as one in four people getting this type of care are covered by Medicaid.
Rep. Mark Takano, a Democrat who chairs the Congressional Equality Caucus, called the move “another cruel, overreaching attack” on transgender youth.
“Decisions about a young person’s care should be between the patient, their parents, and their provider – not politicians,” Takano wrote.
Trump first took action against gender-affirming care for minors with an executive order in January 2025. In April 2025, Oz told states not to use Medicaid funding for surgeries or hormone treatment.
In December, HHS Secretary Robert F. Kennedy Jr. announced his department was beginning an administrative process to end funding for hospitals who provide gender-affirming surgeries.
The Food and Drug Administration, which regulates medical devices, also sent warning letters to manufacturers of breast binders telling them not to market their devices to children with gender dysphoria.
Connecticut Children’s Medical Center in Hartford has agreed to stop providing gender-affirming medical treatments to minors, including puberty blockers and cross-sex hormones, as part of a settlement with the U.S. Department of Justice.
The DOJ announced the agreement Wednesday as part of its ongoing national investigation into gender-affirming care for children and adolescents.
According to the DOJ, Connecticut Children’s agreed not to perform gender-affirming procedures or surgeries on minors. The hospital also agreed to pay a monetary penalty and provide an additional $500,000 in medical care for people who previously received gender-affirming treatment at the facility.
The DOJ alleged that the hospital violated federal law in connection with its pediatric gender-affirming services.
“The Department of Justice will stop at nothing to protect America’s children,” Associate Attorney General Stanley Woodward said. “This resolution is a reminder to hospitals, medical providers, and pharmaceutical companies that the Justice Department will vigorously enforce federal law, especially where the lives of children are endangered.”
Connecticut Children’s confirmed the settlement in a statement and said the agreement allows the hospital to remain focused on its mission of improving children’s health.
The hospital said protecting patient privacy was its “foremost concern” throughout the process and that the matter was resolved without providing protected patient information to the federal government.
“We have complied and will continue to comply with all federal and state laws,” the hospital said.
The settlement is the latest agreement reached by the DOJ involving gender-affirming care for minors.
In May, Texas Children’s Hospital agreed to establish a “detransition clinic,” according to the DOJ. In June, the Cleveland Clinic Foundation agreed to provide detransition care.
The agreements come amid a broader federal effort to investigate and restrict gender-affirming care provided to children and adolescents.
The New Jersey General Assembly passed new legislation on Tuesday, the last day of Pride Month, that strengthens the protections around gender-affirming health care, reproductive care, including abortion and IVF, and more. The bill now sits on Gov. Mikie Sherrill’s (D) desk awaiting her signature, which it is expected to receive.
The passage is a win for the trans community. The bill passed the same day the Supreme Court dealt a blow to trans rights with its West Virginia v. B.P.J. ruling.
Speaking with the New Jersey Monitorafter the vote, Jennifer Williams, a Trenton city council member who is trans, said, “New Jersey is a great, liberty-loving state that will remain a safe haven for those who want to live happy, productive lives while accessing medically necessary and proven medical care.”
The bill’s passage comes after a long battle from LGBTQ+ advocacy groups, including Garden State Equality. In a statement, Lauren Albrecht, the organization’s senior director of advocacy & organizing, said, “By passing this bill, the Legislature has sent the message that bodily autonomy and access to medically necessary, best-practice healthcare are New Jersey values. As other states and the federal government attack reproductive and trans healthcare, we have made it clear that the Garden State will protect both the lifesaving care itself and the people who provide it. Our priorities now will be to ensure Governor Sherrill swiftly signs this legislation and, afterwards, to educate healthcare providers on these new and bolstered protections.”
The new legislation makes no changes to what medical care is or isn’t available in the state, but protects access for all to the services that are already provided.
A major aspect of the bill protects providers and patients from being prosecuted by other states, affirming that those who receive or provide care in New Jersey are solely subject to the state laws of New Jersey and to federal law.
That applies not just to citizens of New Jersey, but to “those who travel to [New Jersey] for health care services,” with the bill noting that all “deserve the ability to safely access health care facilities in this State and the critical reproductive health and gender-affirming care services that they provide.”
This prevents states from prosecuting their residents who have crossed state lines to receive healthcare that is banned in their state but legally protected in New Jersey. The authors of the bill point to the fact that since Roe v. Wade was overturned in 2022, 21 states have either banned or restricted abortion access. Since then, New Jersey has seen a 30% increase in out-of-state patients.
They also highlighted Alabama’s ruling that embryos are “extrauterine children” and the threat that sort of ruling could pose to IVF fertility treatments, which are often used by same-sex couples to build their families. New Jersey has legally protected the right to access IVF treatment.
While New Jersey is the latest blue state to pass such a bill, theirs includes an aspect that hasn’t been seen in other legislation. The bill includes prohibitions on “interference with reproductive or gender-affirming health care services.” That includes inflicting injury, physically obstructing them, defacing property, recording people accessing care within 100 feet of the entrance to a clinic, or distributing such recordings.
The legislators cite the fact that since Roe was overturned, there has been a 538% increase in obstructions to reproductive health facilities, and in 2023, there were 23 reported violent incidents and threats made to gender-affirming care providers. The legislation states, “This act is intended to ensure that anti-abortion and anti-LGBTQ+ persons cannot harm patients or providers.”
Mirroring a proposed shield law in California, the bill also requires the written consent of a patient or their guardian for any of their medical records to be provided to an out-of-state authority. A similar shield law in New York was the reason that patients were informed when NYU Langone Health received a criminal subpoena, insisting that they hand over the medical records for minors who received gender-affirming care at the institution.
The Texas attorney general has secured an unusual settlement over child transgender care that compels Texas Children’s Hospital to create the nation’s first ever “detransition clinic” in addition to paying the state $10 million.
According to Attorney General Ken Paxton, the multidisciplinary clinic would offer medical care to patients “who were subjected to ‘gender-transition’ procedures.” The care would be free to patients for the first five years of the clinic’s operation. The move follows an investigation that began in 2023 by the attorney general’s office into Texas Children’s Hospital in Houston. That same year, Gov. Greg Abbott signed Senate Bill 14 that bars transgender children from receiving puberty blockers and hormone therapies.
Gender-affirming care is an umbrella term for the treatment of gender dysphoria, or the discomfort that comes when someone’s gender identity does not align with the sex they were assigned at birth. Gender-affirming care ranges from “socially transitioning” — using different pronouns or dressing differently — to puberty blockers, hormone therapy and surgical interventions.
“Today is a monumental day in the fight to stop the radical transgender movement,” Paxton said in a statement issued Friday. “I applaud Texas Children’s Hospital for changing course and committing to being a part of the solution by agreeing to form a first-of-its kind Detransition Clinic that will help provide free care to those who have been victimized by twisted, morally bankrupt transgender ideology.”
Texas Children’s will fund all services provided through the “detransition clinic” for the first five years.
The settlement also requires the hospital to pay $10 million for billing Texas Medicaid after the state accused the hospital of illegal ‘gender-transition’ interventions, including by using false diagnosis codes. It also required Texas Children’s to terminate and revoke the medical privileges of five physicians. Paxton and the hospital have not released the name of the physicians or a copy of the settlement.
Texas Children’s, the nation’s largest pediatric hospital, said in a statement that it made the “difficult decision” to settle with the attorney general’s office to close a legal chapter that has been, “wrought with falsehoods and distractions.”
The hospital said it spent three three years producing more than 5 million documents to both the state and the U.S. Department of Justice.
“All reviews and investigations continue to support the facts – we have been compliant with all laws,” the hospital statement said. “To be clear – we are settling to protect our resources from endless and costly litigation … We stand proud knowing we will always put our purpose over politics and that we have and will continue to follow the law.”
The Texas Medical Association and Texas Hospital Association declined to answer questions for the story.
Unclear what services clinic will provide
Texas Children’s, one of the world’s leading pediatric hospitals based in the heart of Houston’s medical center, did not say how it will roll out its clinic or what services it will provide, though the hospital said in the statement that the clinic will include “supportive, multidisciplinary services we already deliver to all patients who need our care.”
Detransitioning is the stopping or reversal of transitioning care by social, medical or legal means, and it is rare for people to regret transitioning after taking hormone therapy and surgical interventions.
On the clinical side, detransitioning could mean stopping hormone treatment or procedures to reverse previous surgeries. Similar to transitioning, detransitioning requires intensive mental health assessments to root out other factors that might be creating the desire to stop transitioning, according to research. Common reasons for destransitioning include lack of family support, financial barriers and social pressure.
When someone chooses to detransition, “it is not normally because of healthcare complications,” said Andrea Segovia, senior field and policy director for the Transgender Education Network of Texas.
Segovia is concerned that access to mental healthcare will not be woven into the clinic’s services. In March, Paxton released an opinion saying that mental health providers licensed by the state cannot provide gender-transitioning care to minors under state law. It’s not clear if Paxton believes state law bars detransitioning mental healthcare as well.
For those who do want to detransition, the resources already exist, said Kellan Baker, senior advisor for the Movement Advancement Project, a national think tank that focuses on LGBTQ policies.
Detransitioning services, although they are rarely needed, can and have been offered properly when accompanied with mental health resources. But Baker said he’s not confident that this clinic, born out of a heated conflict between a hospital and the attorney general, has the best intentions for the transgender community.
“Texas Children’s is not creating this clinic — the Texas attorney general is creating it,” Baker said. “A clinic created by a politician via legal intimidation is not in the best interests of any patient. Doctors should be the ones making decisions about how to provide medical care, not politicians.”
‘Resource that no one is asking for’
Brad Pritchett, CEO of Equality Texas, a nonprofit that advocates for the LGBTQ community, said in a statement that the attorney general is “blackmailing a hospital system into creating a resource that no one is asking for.”
Pritchett said Texas’ politically-motivated detransition clinic “ignores the actual science and years of data about the overwhelming benefits of gender-affirming care.”
Several medical associations including the American Medical Association, American Academy of Pediatrics, American Academy of Child and Adolescent Psychiatry and American Psychiatric Association, have supported evidence-based gender-transitioning care as appropriate and medically necessary for children.
Pritchett added that it is “embarrassing that a hospital once revered for its care has lost its integrity and put politics over patients.”
Dallas state Rep. Jessica González who chairs the Texas House LGBTQ Caucus said in a statement that the settlement is “shameful, and is the furthering of an agenda to eradicate transgender people from the eyes of society.”
Transgender people make up about 1% of the population, which is why, Segovia said, it is “infuriating” that the state is creating the detransition clinic as access to other healthcare services are struggling — such as rural hospitals and reproductive care.
Texas Children’s has to fully fund the clinic for five years, which will take away attention and limited resources from the hospital’s other departments such as care for children with cancer and infants with heart conditions, González said.
“Using a settlement to compel a hospital to build an ideologically framed clinic opens the door to more state interference in medical practice, more dangerous stigmatization that truly harms
young Texans, and, sadly, more lives lost in our nation’s suicide epidemic,” said González, one of the few only queer representatives in Texas.
Houston state Sen. Molly Cook, who is also openly queer, said Paxton is manufacturing a political spectacle because providers know how to help someone detransition and the state doesn’t need a clinic to train them on it.
“This is an asinine waste of money that is typical of Texas’s out-of-touch statewide leadership,” Cook said in a statement. “Texas Children’s already provides care for patients who choose to change a course of treatment.”
The need for such a clinic in Texas is made even smaller by the fact that the state’s ban on gender-transitioning care for minors has resulted in very few Texas children receiving such care statewide.
The five doctors that Paxton said Texas Children’s will need to fire adds to the four doctors he’s already sued to stop providing gender-affirming care. He’s also sued Children’s Health System of Texas, headquartered in Dallas, accusing them of violating SB 14. Some parts of Texas already suffer from a pediatric endocrinologist shortage in the wake of SB 14.
Segovia with the Transgender Education Network of Texas said she’s worried that other states will follow Texas’ lead in forcing more of these clinics to open.
“It’s terrifying what other states will take from this.”
McGill University in Quebec has denied gender-affirming care to at least two trans American students since March, when the school adopted a preemptive policy denying hormone replacement therapy over fears the Trump administration would retaliate, two sources say.
The new policy is an embarrassment, said an American staffer for The Montreal Trans Patient Union (TPU), who spoke to CBC on the condition of anonymity.
“These are American laws. American laws don’t apply in Canada,” they said.
The staffer and another member of TPU, Emma Gimbert, were at a meeting at McGill’s Student Wellness Hub in March when doctors brought up the change in policy.
“They said they wouldn’t be prescribing HRT to American citizens who were under 19 because of the executive order that Donald Trump issued,” Gimbert said.
The student was referring to Trump’s executive order, Protecting Children from Chemical and Surgical Mutilation, issued a year ago in January, which directs federal agencies to carry out the American president’s crusade against transgender identity across the U.S. government.
“If you told me a month ago that a U.S. executive order would be influencing how doctors do their job across the border, I would have been like, no, that can’t be the case,” Gimbert said.
Canadians have been overwhelmingly critical of Trump and his trolling threats to their sovereignty since the start of his second term. McGill’s decision, from fiercely independent Quebec, no less, would seem antithetical to the rest of Canada’s posture facing Trump.
About 1000 Americans are currently enrolled at McGill, a public research university in Montreal known as “the Harvard of Canada.” Among nearly 40,000 students, a high proportion are from abroad.
Adding to the absurdity of a Canadian university bowing down to an American president, the decision may have been based in part on a clerical error.
The TPU staffer explained.
“The doctors said the reason for this was specifically the fact that the form the U.S. released had provisions for targeting Canadian doctors and taking down their information.”
The document in question was a snitch form issued by the U.S. Department of Health and Human Services to report health professionals administering gender-affirming care to minors in the U.S.
The drop-down menu, like many forms online, included the word “province” along with “state.”
Panicked administrators at McGill apparently thought that word put a target on Canadian medical professionals’ backs. HHS had even removed it by the time McGill denied the HRT to their American students.
McGill would neither confirm nor deny the existence of a policy barring Americans from gender-affirming care for fear of retaliation by Trump.
“Access to gender-affirming care is available to McGill students, including international students,” the university said in a statement.
“The medical aspects of this care are provided by licensed physicians. These decisions are not made by the university,” the school added, in a probably doomed effort to evade accountability from Canadians incensed at McGill’s failure to defend their independence.
“I think it’s definitely important for them to acknowledge what’s been going on because the way they’re currently treating this, it’s kind of covert,” Gimbert said.
“We know this is something that they’re aware of. It’s just not something that they’re publicly talking about.”
Added the American TPU staffer: “I mean, we don’t say that 18-year-old Americans can’t buy alcohol here because the drinking age in the U.S. is 21.”
Ohio Rep. Josh Williams (R-Sylvania Twp.) has introduced his latest bill in his crusade against transgender Ohioans.
Williams introduced HB 838 last Thursday. The bill would prohibit Medicaid from covering most gender-affirming surgeries and procedures for transgender Ohioans and ban state and local municipalities from providing a contract to their employees that includes “coverage, benefits, or services for gender reassignment surgery.”
The legislation also stipulates that if these benefits are offered, the cost would then be subtracted from the local authority’s “local government fund payments,” the revenue-sharing portion of the state’s General Revenue Fund.
The bill has not yet been assigned to a committee.
Williams has broken a record, introducing more than 100 bills in a single General Assembly as he runs for a spot in the U.S. House of Representatives.
Six of those bills are explicitly anti-LGBTQ+, complementing his public statements that it would be “harmful to society” to affirm trans identity.
HB 249 (“The Indecent Exposure Modernization Act”), which would ban drag and gender performance in public spaces where minors are present. (Status: The bill passed the Ohio House and now moves to the Ohio Senate.)
HB 262, to designate “Natural Family Month,” to celebrate only heterosexual married couples with children. (Status: The bill is sitting in a House committee; three hearings have been held.)
HB 693 (“The Affirming Families First Act”), to grant protections to parents who reject their trans children. (Status: The bill is sitting in a House committee; two hearings have been held.)
HB 796 to ensure that all incarcerated people in state custody are housed according to the state’s definition of “biological sex.” (Status: The bill has been introduced, but not assigned to a committee.)
HB 798 (“The Privacy Protection Act”) that would limit trans Ohioans’ access to public bathrooms and ban Ohioans from being able to change the sex marker on birth and death certificates. (Status: The bill has been introduced, but not assigned to a committee.)
In the Cleveland suburb of Lakewood, the city’s robust “Gender Freedom Policy” would protect LGBTQ+ employees from the effects of HB 838.
The policy was introduced by Council President Sarah Kepple and out LGBTQ+ Councilmember Cindy Strebig, and will allow the city to provide medical coverage for transgender employees and covered family members who seek gender-affirming care, “even if such care must legally be provided outside the State of Ohio.”
“This is another attempt by the Republican led and out of touch state government to draw attention away from their continued failure to serve Ohioans,” Strebig told The Buckeye Flame. “I will continue to fight for my community and the dignity and respect of all people.”
Dara Adkison, executive director of TransOhio, said that HB 838 is just the latest bill in an “exhausting pattern of a single politician repeatedly targeting transgender Ohioans instead of addressing the real challenges facing our state.”
“Continued increasing of restrictions and limitations to healthcare undermines the safety, health and wellbeing of not only trans Ohioans but everyone,” Adkison said.
Adkison called HB 838 “reprehensible,” but reminded Ohioans that the bill was just introduced and is not law.
“Everyone deserves the ability to make informed decisions about their own healthcare, and every municipality deserves to maintain the authority over what will be covered by city employee insurance plans,” Adkison said.















You must be logged in to post a comment.